


A claim can be documented, coded correctly, and payable, yet earn nothing because it reached the payer after the deadline. Late claims rarely announce themselves and return months later as denials that appeals may not reverse. TMS Billings’ Revenue Cycle Management Services center on claim accuracy and denial prevention, and this guide explains timely filing limits by insurance. A timely filing limit is the maximum time a payer allows between the date of service (DOS), or another triggering event, and receipt of a claim. You will learn how limits differ by payer, when the clock starts and stops, how corrected claim and appeal windows work, and how to prevent and recover from missed deadlines.
Why Timely Filing Limits by Insurance Matter to Your Practice
What is timely filing in medical billing? Timely filing is the payer-imposed deadline for receiving a claim, and a claim received after it is usually denied regardless of clinical or coding accuracy.
Each timely filing limit differs by payer type (federal program, state program, or commercial plan), the provider’s participation contract, network status, and state law. Participating (in-network) and non-participating (out-of-network) providers may face different windows under the same payer.
A timely filing denial is usually reported with claim adjustment reason code (CARC) 29 under the CO group code, which generally places the loss on your practice. The revenue is often unrecoverable, so confirm contract and state-law treatment with compliance counsel.
MGMA’s revenue cycle benchmarking and best-practice resource supports practice leaders who track revenue cycle management (RCM) performance. If you use a billing vendor, review medical billing pricing models to confirm who bears responsibility for missed deadlines and whether fees align with collections secured.
Timely Filing Limits by Insurance: Payer-by-Payer Comparison at a Glance
Timely filing limits by insurance are the deadlines each payer sets for receiving a claim after the date of service. Original Medicare allows 12 months, Medicaid rules are set by each state, and commercial limits depend on the participation contract, so confirm the current limit before billing.
The timely filing limit for Medicare is set by federal rule, while other payers publish their own windows. The table lists commonly published limits and is not a substitute for the payer contract.
| Payer | Commonly Published Filing Window | Verify Before You Rely on It |
|---|---|---|
| Original Medicare (Parts A and B) | 12 months (one calendar year) from the date of service under federal rules | Measured by the Medicare contractor’s receipt date; exceptions are limited; claims rejected as unprocessable are not considered filed |
| Medicaid fee-for-service | Set by each state; the federal rule requires a submission deadline no later than 12 months from the DOS | The state provider manual for your program and claim type |
| Medicaid managed care and Medicare Advantage plans | Set by the plan contract and often different from the fee-for-service rule | The provider agreement and plan manual, plan by plan |
| UnitedHealthcare (commercial) | Commonly published as 90 days from the DOS for participating providers | The participation agreement, state law, and the current Care Provider Administrative Guide |
| Cigna | Commonly published as 90 days in-network and 180 days out-of-network | The Cigna provider manual and your contract |
| Aetna | Contract-specific; no single figure applies to every plan | The participation agreement and Aetna provider manual |
| Blue Cross Blue Shield and Anthem plans | Varies by licensee and product | The plan-specific provider manual |
| TRICARE | One year from the DOS, or from discharge for inpatient claims | The regional contractor’s provider handbook and its timely filing waiver rules |
Workers’ compensation, auto, and other liability carriers follow state law and their own carrier rules, and limits change, so confirm current terms in each contract. Medicaid deadlines derive from the federal Medicaid regulation (42 CFR 447.45), which requires each state agency to set a submission deadline no later than 12 months from the DOS.
Limits verified September 2026.

When the Timely Filing Clock Starts and Stops
When does the timely filing clock start? It generally starts on the date of service and stops when the payer receives a claim it accepts for processing, not when your practice sends it.
Because timely filing limits by insurance are generally measured by payer receipt, a postmark or clearinghouse upload date does not prove compliance. Clearinghouse acceptance is not payer acceptance, and a claim rejected as unprocessable is generally not treated as filed. Medicare measures receipt at the Medicare Administrative Contractor (MAC).
Span-of-service claims follow a second rule: Medicare Part B uses the “from” date, while Part A uses the “through” date. On secondary claims, coordination of benefits (COB) determines the sequence, and many contracts run the clock from the date of the primary payer’s explanation of benefits (EOB).
Claims held for retroactive eligibility, prior authorization, or payer enrollment usually keep aging unless the payer agrees otherwise in writing. Weigh the credentialing cost of an enrollment lapse against keeping enrollment current, because held claims can exhaust the timely filing deadline.
The CMS Medicare Claims Processing Manual (Pub. 100-04), Chapter 1, Section 70, governs Medicare time limits for filing claims, and each commercial manual states its own timely filing limit.
Corrected Claims, Resubmissions, and Appeal Windows
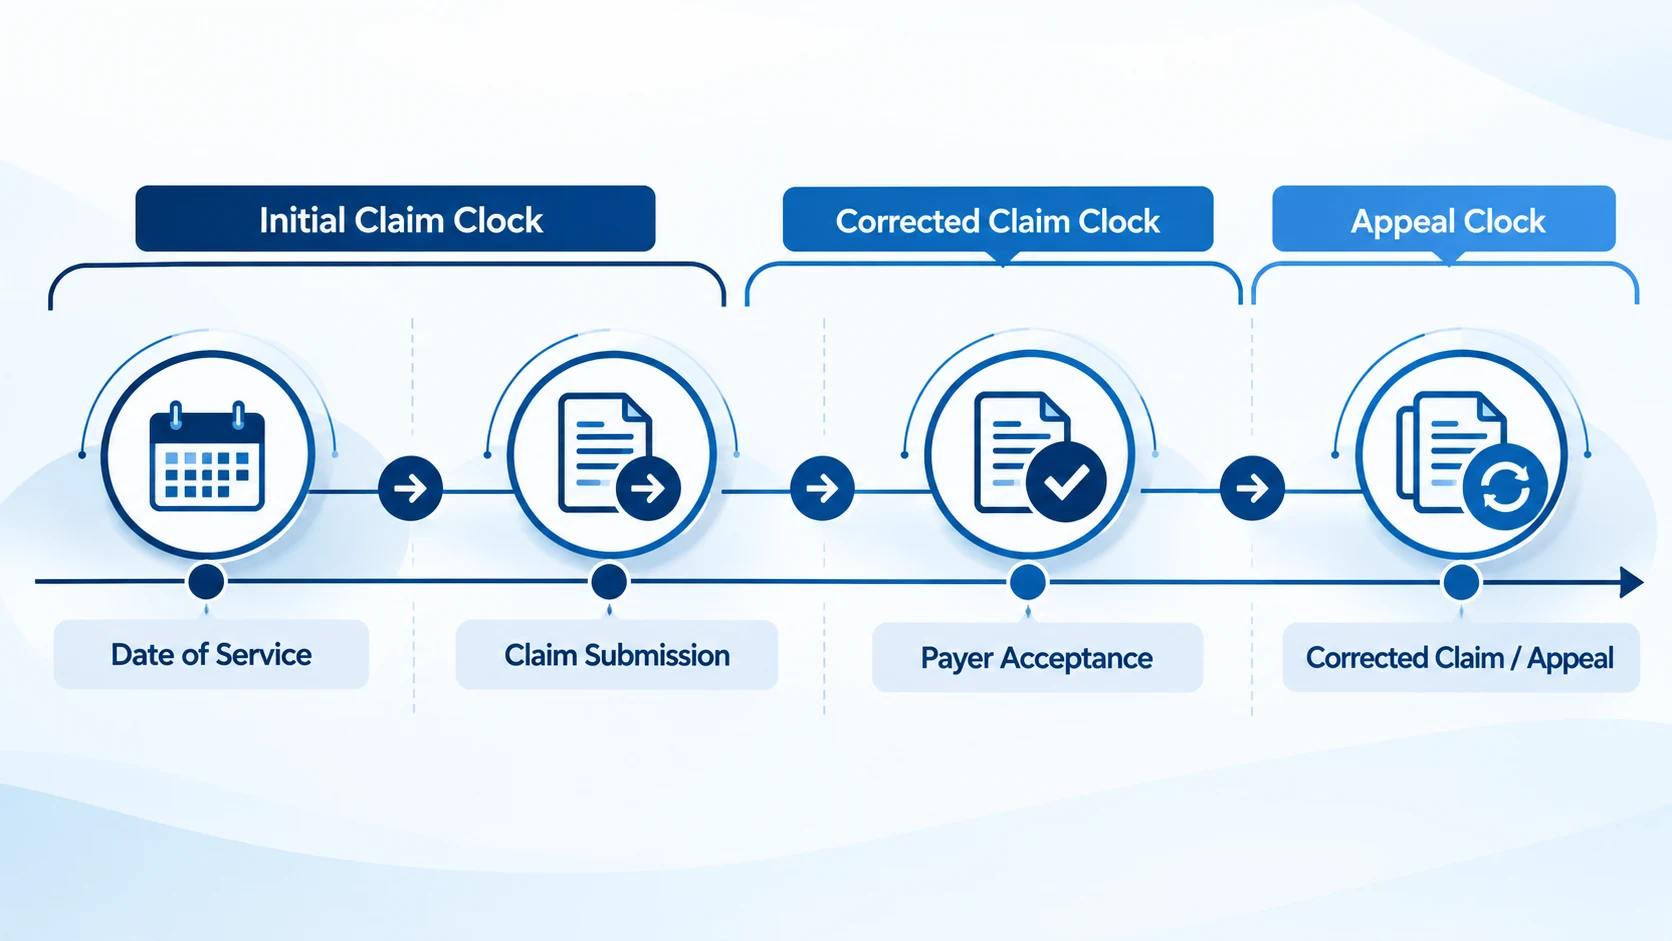
The timely filing limit for corrected claims does not automatically reset the original clock, and neither does an appeal, because payers measure the initial claim, the resubmission, and the appeal separately. Your practice should track three clocks.
Corrected claim windows may run from the original DOS, the remittance date, or a payer request for information. The timely filing appeal window usually runs from the remittance or denial date and is often shorter than the initial filing limit, and some payers require reconsideration before a formal appeal.
Payers revise these rules. UnitedHealthcare’s 2026 Care Provider Administrative Guide updated its corrected claim timely filing requirements, so recheck timely filing limits by insurance in each current manual and attribute any day count to that payer.
Accurate first-pass coding protects filing time. Your clean claim rate is the share of claims accepted and paid on first submission, and it rises as resubmissions fall. The American Medical Association maintains CPT codes, and CMS maintains HCPCS Level II codes and NCCI edits. AAPC’s Certified Professional Coder (CPC) certification page describes the coding-competency standard for coders whose accuracy limits rework.
Procedure-heavy specialties illustrate the risk: pathology-dependent coding, common in gastroenterology medical billing services, often produces resubmissions while the original clock keeps running.
Common Causes of Missed Filing Deadlines and How to Prevent Them
Most missed deadlines are workflow failures rather than payer errors, and each one has a preventable cause.
Delayed charge entry and coding holds. Charges wait in the practice management (PM) system for documentation, pathology, or coder review. Prevention: review a weekly unbilled-charge report against each payer’s limit to expose charge capture and charge entry lag.
Clearinghouse rejections left unworked. Rejected claims are not filed claims. Prevention: work a daily rejection queue and review 277CA claim acknowledgment reports to confirm the payer accepted each submission.
Enrollment and credentialing gaps. Claims for a new provider wait on payer enrollment. Prevention: confirm provider credentialing and enrollment before scheduling patients, and use Credentialing Services where internal capacity is limited.
Eligibility, coordination of benefits, and authorization errors. The wrong payer is billed first, and the correct payer is found after the window closes. Prevention: complete eligibility verification at registration and update COB promptly, which also keeps patient balances accurate.
Vendor, PM system, and staffing transitions. Handoffs create backlogs. Prevention: inventory deadlines before transitions and sign a Business Associate Agreement (BAA) with vendors handling protected health information, following HHS Office for Civil Rights sample provisions; confirm terms with counsel.
Proof of Timely Filing, CO-29 Denials, and Exceptions
A CO-29 denial is not always final: documented proof that the payer received the claim before the deadline can support an overturn, while formal exceptions are narrow and payer-specific.
CARC 29 reports that the time limit for filing has expired, and the CO group code generally places financial responsibility on the provider under the contract. The electronic remittance advice (ERA) displays the CARC and any remittance advice remark code (RARC). X12 maintains both code sets, and CMS’s Health Care Payment and Remittance Advice resource explains them.
How to prove timely filing: keep the clearinghouse acceptance report or 277CA, the payer portal confirmation, an earlier ERA showing a rejection or denial, a certified-mail receipt for paper claims, the primary payer’s EOB for secondary claims, and a dated submission log, organized by claim. Proof of timely filing requirements differ by payer, so confirm each policy.
How to appeal a CO-29 denial: confirm the denial against the DOS and the payer’s receipt date, gather the proof, file within the payer’s appeal deadline with a written explanation, and track the outcome. Medicare handles untimely filing through limited exceptions rather than standard appeals. Elsewhere, exceptions generally cover payer error, retroactive eligibility, or a delayed primary payer response, and each payer sets its own policy. Outcomes depend on the proof on file, and no appeal is guaranteed.
How to Track Timely Filing Limits by Insurance in Your Billing Workflow
How to track timely filing deadlines: record each payer’s timely filing limit from its contract, load it into the PM system with alerts ahead of the deadline, and review unbilled and rejected claims on a fixed cadence.
Build a payer deadline matrix from your contracts, separated by participating and non-participating status. Set alerts at fixed intervals before each deadline, and keep work queues for unbilled charges, rejections, and claims awaiting a primary payer response. Prompt payment posting surfaces denials early. Re-verify every limit after contract renewals, payer bulletins, and each January manual update.
Track key performance indicators (KPIs): clean claim rate, charge entry lag, days in A/R (accounts receivable), denial rate, and the share of denials coded CO-29, compared against a baseline set before corrective action. Treat any target as illustrative, because payer mix and case mix affect results. HFMA’s MAP Keys are the industry-standard KPI set for measuring revenue cycle performance. Practices considering outside support for deadline monitoring can review current service pricing.

How TMS Billings Supports Timely Filing Compliance
TMS Billings applies a deadline-first workflow: a payer-specific deadline matrix, daily clearinghouse rejection work, unbilled-charge monitoring, credentialing coordination, appeals supported by proof of timely filing, and monthly KPI reporting with corrective actions. Outsourced denial management can shorten the resubmission cycle compared with in-house handling, although no percentage is guaranteed.
The same workflow can run entirely in-house. Our RCM and billing support team assists practices that want added capacity, an independent review, or ongoing help with timely filing limits by insurance, A/R follow-up, and payment posting.
A multi-provider practice held charges for a newly credentialed provider while enrollment was pending, and several claims aged past a commercial payer’s window and denied as CO-29. After adding a payer deadline matrix, alerts, and a weekly unbilled-charge review, timely filing denials declined and eligible claims were appealed with saved clearinghouse proof of submission.
Key Takeaways
- Timely filing limits by insurance vary by payer, contract, and state, so every limit should be verified against the current source.
- Original Medicare allows 12 months from the DOS, while Medicaid follows a federal 12-month maximum with state rules controlling.
- The clock generally stops on payer receipt of an accepted claim, and corrected and appealed claims run on separate windows.
- Saved clearinghouse reports, ERAs, and dated submission logs can support an overturn when a payer denies a claim as untimely.
- Most missed deadlines stem from workflow gaps, which a payer deadline matrix, alerts, and KPI monitoring help prevent.
Related Reading: Explore billing cost and revenue-cycle coverage in medical billing services cost in California, medical billing services cost in Texas, and mental health billing cost comparison.
Final Thoughts
As a physician owner or practice administrator, you protect revenue by treating payer filing deadlines as a controlled process rather than a calendar reminder. Understanding timely filing limits by insurance, and building a workflow that enforces them, prevents losses that appeals cannot always recover. Payer contracts, regulations, and compliance requirements change periodically, so confirm current requirements with your payers, vendor, or counsel. Book a Free Consultation to review your deadline controls with our team.


